

Tired of Frequent Bathroom Trips? Understanding Urgency, Frequency and Bladder Control

Understanding the Frustration of Incontinence and Frequent Bathroom Trips!
Having to find a toilet again and again can make ordinary parts of the day surprisingly difficult.
You may find yourself planning journeys around toilet stops, waking during the night to urinate, looking for a bathroom as soon as you arrive somewhere, or worrying that a sudden urge will leave you without enough time to get there.
The two most common types are stress incontinence and urge incontinence, and both often result from weakened pelvic floor muscles.
Frequent trips to the toilet can happen for several reasons. Sometimes the problem is simply drinking more fluid than usual. At other times, frequent urination or urgency can be associated with an overactive bladder, urinary infection, certain medicines, prostate problems or other health conditions.
If you are also experiencing leakage, it is useful to understand what type of urinary incontinence may be involved.
This guide explains the difference between urinary frequency, urgency, urge incontinence and stress incontinence, what can contribute to these symptoms, and where pelvic-floor treatment fits into the wider picture.
Frequent Urination Is Not Always the Same as Incontinence
Frequent urination and leaking urine are related but different problems.
Urinary frequency means needing to pass urine often.
Urinary urgency describes a sudden or difficult-to-defer need to urinate.
Urge incontinence is leakage that happens with, or immediately following, a sudden urge to urinate.
Stress urinary incontinence is leakage associated with activities that generally put pressure on the bladder, such as coughing, sneezing, laughing or exercising.
Some people experience more than one type of symptom. NICE refers to this combination as mixed urinary incontinence when both stress and urgency symptoms are present.
That distinction matters because the best way to manage symptoms depends on what is causing them.
Why Do I Keep Needing to Go to the Bathroom?
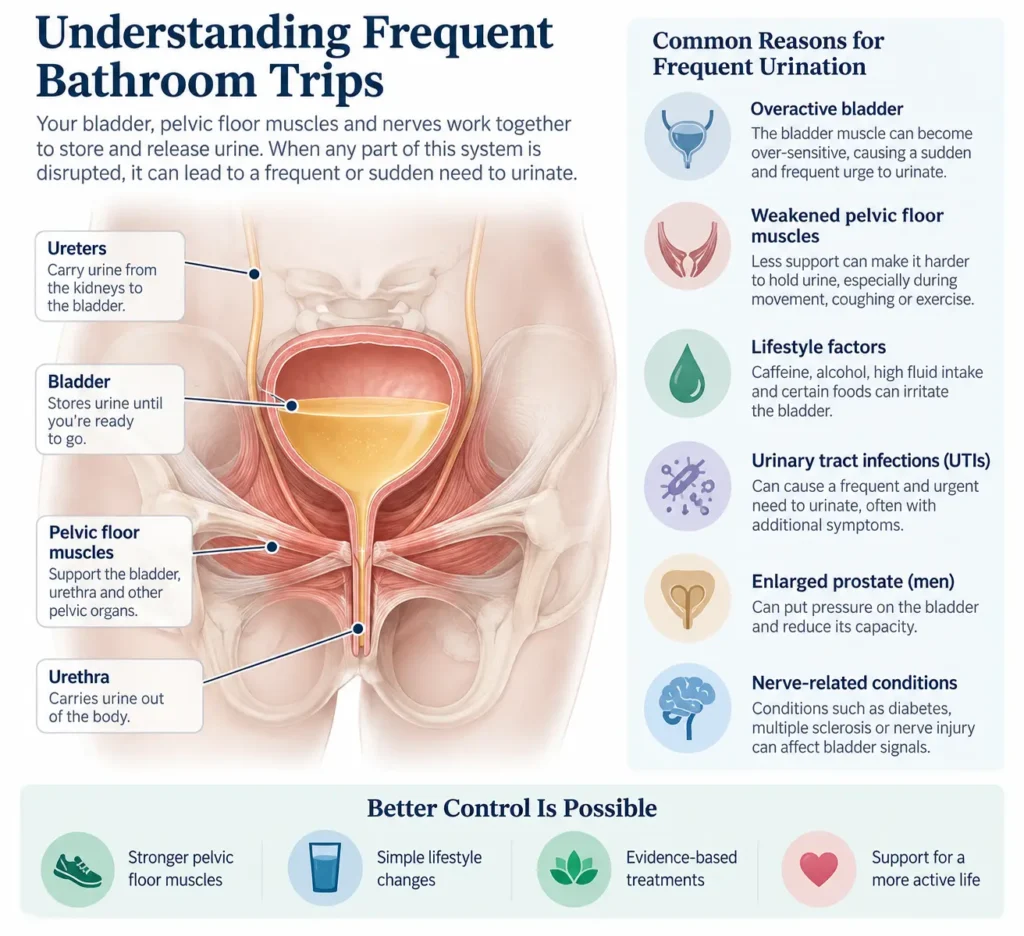
There is no single explanation for frequent bathroom trips.
How often someone needs to urinate can change with fluid intake, caffeine, alcohol and other everyday factors. Certain medicines can also affect urinary symptoms.
Other possible causes include urinary tract infections, overactive bladder, loose pelvic floor muscles, prostate-related problems in men, diabetes and other medical conditions.
In men, NICE groups urgency, frequency, urgency incontinence and getting up at night to urinate under storage lower urinary tract symptoms. These symptoms can have different causes, including changes involving the prostate, bladder or urinary tract.
That is why persistent or troublesome urinary symptoms should not automatically be attributed to weak pelvic-floor muscles.
What Is an Overactive Bladder (OAB)?
Overactive bladder is a group related to urinary symptoms in which urgency is a central feature. It can also involve increased daytime frequency and waking during the night to urinate.
An overactive bladder does not necessarily mean that the pelvic-floor muscles are weak.
The bladder, nervous system, pelvic floor and urinary tract all have roles in normal bladder storage and emptying. Problems affecting any of these areas can contribute to urinary symptoms.
For women with urinary incontinence or overactive bladder, NICE recommends an assessment that considers possible contributing factors and other diagnoses. A bladder diary covering at least three days can also be useful during initial assessment.
What Is Urge Incontinence?
Urge incontinence occurs when urine leakage is associated with a sudden, difficult-to-defer urge to urinate.
You might recognise it as:
- suddenly needing the toilet with very little warning
- rushing to the bathroom because the urge feels difficult to hold
- leaking before reaching the toilet
- needing to know where the nearest toilet is when you are away from home
- waking during the night because of urinary urgency
The experience can be frustrating, particularly when the urge arrives at inconvenient times.
It is worth remembering that urgency and urge incontinence are not simply a matter of having a weak pelvic floor. Several contributing factors can play a role, which is why assessment matters when symptoms persist.
What Is Stress Incontinence?
Stress urinary incontinence is different.
The leakage occurs when physical pressure on the bladder increases. Common examples include:
- coughing
- sneezing
- laughing
- lifting
- running
- jumping
- exercising
Pelvic-floor muscle function may also contribute to stress incontinence.
For women with stress or sometimes even for mixed urinary incontinence, NICE recommends supervised pelvic-floor muscle training as a first-line treatment for at least three months.
That recommendation is different from saying that every form of electromagnetic stimulation should be used as a first-line treatment.
Could Weak Pelvic-Floor Muscles Be Part of the Problem?
The pelvic floor helps support the bladder and other pelvic organs and contributes to urinary continence.
Pelvic-floor muscle training is an established part of managing some forms of urinary incontinence. NICE recommends supervised pelvic-floor muscle training as the first-line treatment or defence mechanism for women with stress or mixed urinary incontinence cases.
However, not every episode of frequent urination means the pelvic floor is weak.
If the main problem is urgency, for example, bladder training and assessing contributing factors may matter more than simply strengthening the pelvic floor.
This is one reason we should be careful about describing any single treatment as the answer to frequent bathroom trips.
What Can You Do About Frequent Bathroom Trips?
The right approach depends on the reason for the symptoms.
For women with urgency or mixed urinary incontinence, NICE recommends bladder training for a minimum of six weeks as a first-line treatment. Bladder training aims to help a person gradually increase the time between toilet visits and develop strategies for managing urgency.
NICE also recommends considering lifestyle measures such as reducing caffeine for women with overactive bladder and reviewing fluid intake where it is unusually high or low.
For men with troublesome lower urinary tract symptoms, NICE recommends an initial assessment that considers possible causes, current medicines, and other health factors. A urinary frequency-volume chart may also be used.
The key point is that treatment should follow the symptoms and their likely cause, rather than assuming every frequent trip to the bathroom has the same explanation.
What About Pelvic-Floor Exercises?
Pelvic-floor muscle exercises can help with some types of urinary incontinence.
They involve deliberately contracting and relaxing the pelvic-floor muscles as part of a structured exercise programme.
NICE recommends supervised pelvic-floor muscle training for women with stress or mixed urinary incontinence and recommends continuing the exercise programme when it is beneficial.
Learning to contract the correct muscles can matter. NICE recommends assessment of pelvic-floor muscle contraction before supervised pelvic-floor muscle training for urinary incontinence in women.
If you have been advised to perform pelvic-floor exercises by a healthcare professional, they should not simply be abandoned because another treatment option is available.
Where Does an EMS Chair Fit In?
An EMS chair uses electromagnetic stimulation to produce repeated contractions of the pelvic-floor muscles while the person remains seated.
This is different from voluntarily performing pelvic-floor exercises.
Research has investigated high-intensity focused electromagnetic therapy for urinary incontinence. A 2025 systematic review and meta-analysis included seven studies. Which involving women with urinary incontinence. The review reported reductions in some urinary-incontinence measures and improvements in some quality-of-life measures, but the findings relate to the specific HIFEM interventions and study populations included in the review.
That evidence is worth knowing about, but it needs to be kept in context.
It does not establish that every electromagnetic chair has the same effect. It also does not establish that an EMS chair is the appropriate treatment for every person who makes frequent bathroom trips.
The type of intervention, equipment, treatment protocol, population studied and outcome being measured all matter.
Does EMS Treat Urge Incontinence?
Research has investigated electromagnetic stimulation in women with urinary incontinence, including symptoms associated with urgency.
However, it would be too strong to say EMS will stop urgency or reduce toilet visits.
NICE’s current guidance for women with urgency or mixed urinary incontinence places bladder training among the first-line non-surgical approaches. NICE also states that electrical stimulation should not routinely be used to treat overactive bladder.
Electromagnetic stimulation and electrical stimulation are not the same intervention, so these recommendations should not be presented as a direct ruling on the specific EMS chair service.
They do, however, reinforce an important principle: EMS should not be presented as a replacement for established assessment and management of overactive bladder symptoms.
Does EMS Treat Stress Incontinence?
Pelvic-floor muscle function is relevant to stress urinary incontinence, and research has investigated electromagnetic stimulation as a way of producing pelvic-floor contractions.
The 2025 systematic review of HIFEM for urinary incontinence found improvements in some measures among the women included in the studies, although the review covered only seven studies and the results should not be generalised beyond the interventions studied.
For women with stress or mixed urinary incontinence, NICE recommends supervised pelvic-floor muscle training as first-line treatment.
So if someone is considering an EMS chair, it is more accurate to describe it as one form of electromagnetic pelvic-floor stimulation that has been investigated in urinary incontinence research, rather than a proven solution for stress incontinence.
What Happens During an EMS Chair Session?
With the Incontinence Direct service, the customer sits on the EMS chair while fully clothed and receives electromagnetic pelvic-floor stimulation.
The stimulation produces repeated involuntary contractions of the pelvic-floor muscles.
The treatment experience can vary from person to person. The relevant equipment instructions, suitability requirements and contraindications should be considered before treatment.
There is no need to describe the treatment as thousands of Kegels, and we do not use a number of contractions as a substitute for evidence of clinical benefit.
Likewise, we do not promise a fixed number of sessions or a particular change in symptoms.
Can an EMS Chair Replace Bladder Training or Pelvic-Floor Exercises?
It should not be presented that way.
Bladder training and pelvic-floor muscle training have specific roles in recognised management pathways. NICE recommends bladder training for women with urgency or mixed urinary incontinence and supervised pelvic-floor muscle training for women with stress or mixed urinary incontinence.
An EMS chair provides a different form of stimulation.
If a healthcare professional has recommended bladder training or pelvic-floor exercises, an EMS session should not be treated as an automatic replacement.
When Should You Speak to a GP?
Frequent urination can sometimes be caused by something that needs medical assessment.
Consider speaking to a GP or another appropriate healthcare professional if:
- the change in your urinary pattern is persistent or troublesome
- you are regularly waking at night to urinate
- you have new or worsening urgency
- you are experiencing repeated leakage
- you have difficulty starting or maintaining your urine stream
- you feel that your bladder is not emptying properly
- you have blood in your urine
- you have symptoms that could indicate a urinary infection
- you have other health symptoms alongside the urinary changes
For women with urinary incontinence, NICE identifies persistent bladder or urethral pain, suspected neurological disease, voiding difficulties, recurrent or unexplained urinary infections and blood in the urine among situations that can require further assessment or referral.
For men with lower urinary tract symptoms, NICE recommends assessment of possible causes, medication and relevant health factors rather than assuming that the symptoms are simply part of ageing.
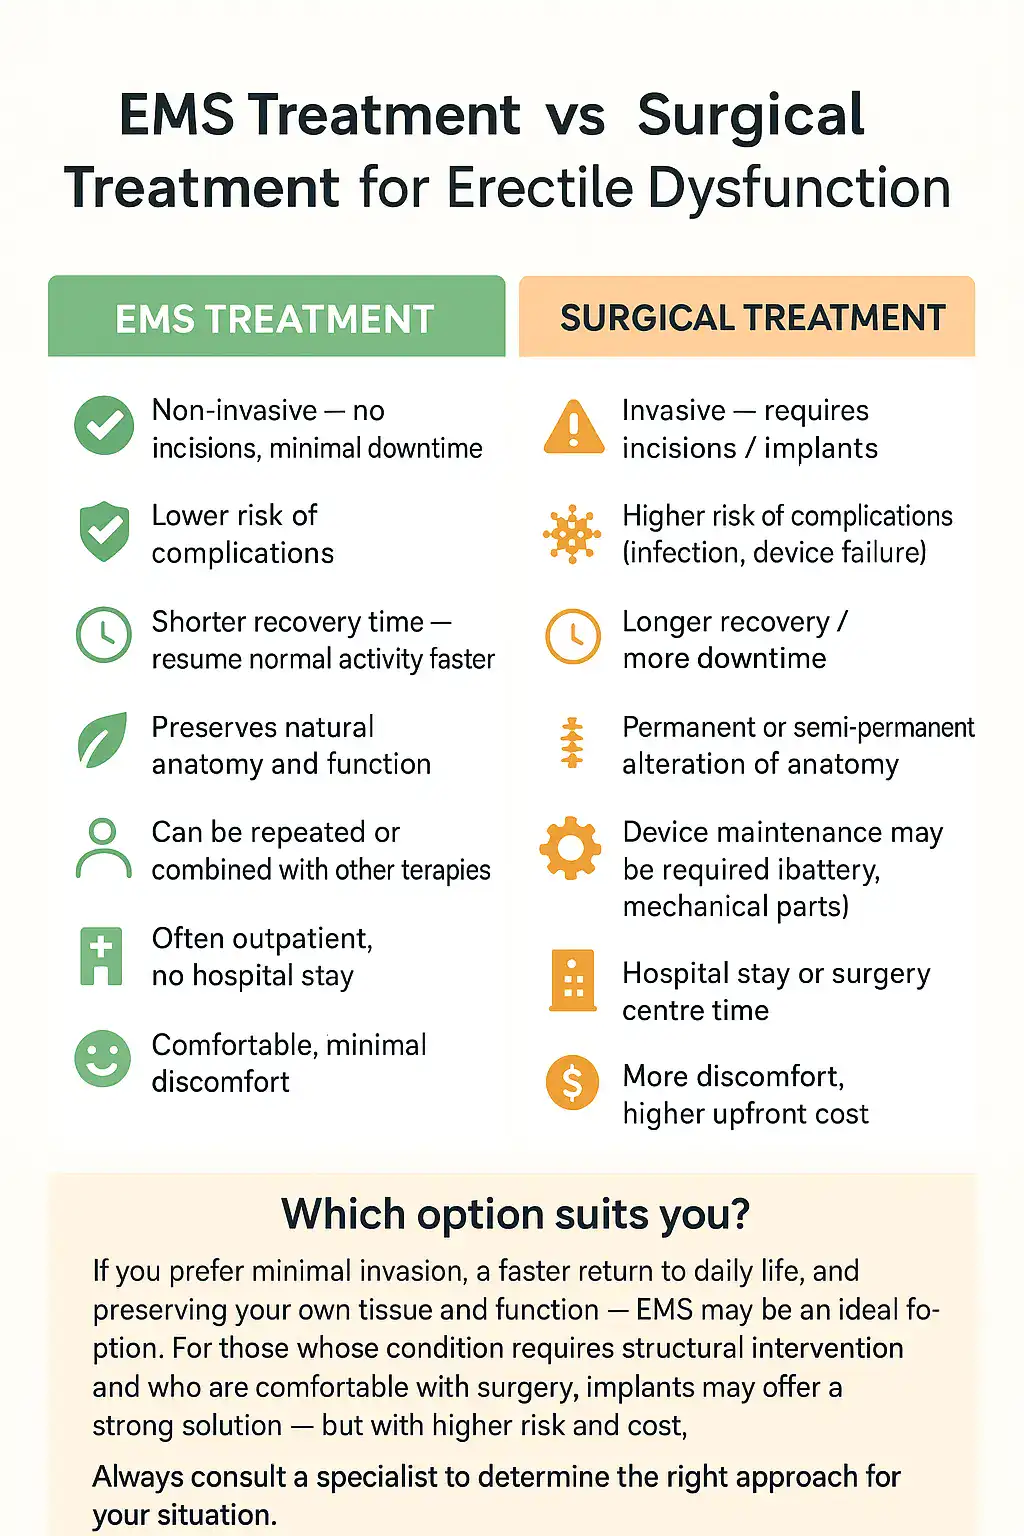
EMS Chair At Incontinence Direct Coventry Vs Surgical Options

FAQs: How EMS (Electromagnetic Seat) Treats Urge Incontinence
Why am I suddenly needing the toilet so often?
There are several possible reasons, including changes in fluid or caffeine intake, urinary infection, overactive bladder, medicines and other health conditions.
If the change persists or is accompanied by other symptoms, it is worth discussing with a healthcare professional rather than assuming the cause.
Why do I keep waking up to pee?
Getting up during the night to urinate is known as nocturia.
It can have several causes, including evening fluid intake and urinary conditions. In men, nocturia is one of the storage lower urinary tract symptoms identified by NICE.
Persistent or troublesome nocturia is worth discussing with a healthcare professional.
Can pelvic-floor weakness cause frequent bathroom trips?
Pelvic-floor function can be relevant to urinary continence, but frequent urination does not automatically mean that the pelvic floor is weak.
Urgency and frequency can have several causes, so it is better to establish what is happening before assuming that pelvic-floor strengthening is the answer.
Is EMS a replacement for bladder training?
No.
Bladder training has an established role in the management of urgency and mixed urinary incontinence in women. NICE recommends bladder training for a minimum of six weeks as first-line treatment in these circumstances.
EMS is a different intervention and should not be presented as an automatic replacement.
How many EMS sessions will I need?
We do not promise a fixed number of sessions for urinary symptoms.
The appropriate schedule depends on the service protocol, equipment and individual circumstances.
Claims that everyone needs six sessions, that improvement should occur after one or two sessions, or that maintenance is required every few months should not be treated as universal medical facts.
Is EMS safe?
Suitability depends on the individual, the specific equipment and its warnings and contraindications.
We do not describe EMS as risk-free or suitable for everyone.
The relevant equipment information should be reviewed before treatment, and anyone with medical concerns should seek appropriate professional advice.
How many times a day is it normal to urinate?
There is no single number that applies to everyone.
Urination frequency depends on factors such as fluid intake, what you drink, medicines, bladder capacity and individual circumstances.
A noticeable change from your usual pattern can be more useful than comparing yourself with an arbitrary number.
Is frequent urination the same as overactive bladder?
No.
Overactive bladder is associated with urgency and may also involve frequency and nocturia. Frequent urination can occur for other reasons as well.
A healthcare professional can help determine what may be contributing to your symptoms.
Can an EMS chair help with bladder symptoms?
Electromagnetic stimulation has been investigated for urinary incontinence, including in a 2025 systematic review of HIFEM studies in women. The review found improvements in some outcomes but was based on seven studies and should not be generalised to every EMS system or every urinary symptom.
Incontinence Direct therefore does not promise that an EMS chair will stop frequent urination, cure urgency or produce a particular result.
Is EMS a replacement for pelvic-floor exercises?
No.
Pelvic-floor muscle training is a recognised first-line treatment for women with mixed urinary incontinence or sometimes stress incontinence.
An EMS chair produces involuntary pelvic-floor contractions, but that does not mean it should automatically replace an exercise programme recommended by a qualified healthcare professional.
How long do EMS results last?
There is not a reliable basis for promising a fixed duration of benefit from EMS for frequent urination or urgency.
Individual responses can differ, and research findings should not be converted into a guaranteed duration for an individual customer.
Can I stop taking bladder medication if I have EMS?
Do not stop or change prescribed medication because you are considering an EMS treatment.
Medication decisions should be discussed with the healthcare professional who prescribed it or another appropriately qualified healthcare professional.
EMS should not be presented as a replacement for prescribed treatment.
What to Do If Frequent Bathroom Trips Are Affecting Your Day
Frequent trips to the bathroom are worth understanding rather than simply putting up with.
Start by paying attention to when the symptoms happen, how often you urinate, whether urgency is involved, whether leakage occurs and whether anything seems to trigger the problem.
For women with urgency or mixed urinary incontinence, bladder training is one of the recognised first-line approaches. For stress or mixed urinary incontinence, supervised pelvic-floor muscle training is also recommended by NICE.
If symptoms are persistent, new or troublesome, appropriate medical assessment can help identify what is causing them.
If you are also considering electromagnetic pelvic-floor stimulation, Incontinence Direct can explain how its private mobile EMS service works, what treatment involves and the relevant suitability information.
The service does not provide a diagnosis and should not replace medical assessment when needed.
Sources & Further Reading
NHS — Urinary incontinence
General information about urinary incontinence, symptoms, causes and treatment.
NICE — Urinary incontinence and pelvic organ prolapse in women: management (NG123)
Guidance covering assessment and management of urinary incontinence and overactive bladder symptoms in women.
NICE — Lower urinary tract symptoms in men: management (CG97)
Guidance covering assessment and management of urinary frequency, urgency, nocturia and other lower urinary tract symptoms in men.
PubMed — Noninvasive High-Intensity Focused Electromagnetic Therapy in Women With Urinary Incontinence: A Systematic Review and Meta-Analysis
A 2025 review of seven studies examining HIFEM in women with urinary incontinence.
Medical Information Notice
This article provides general information about frequent urination, urinary urgency, urinary incontinence and electromagnetic pelvic-floor stimulation. It is not a diagnosis and does not replace advice from a GP or another appropriately qualified healthcare professional. Evidence discussed in this Incontinence Direct article relates to specific interventions and study populations. Research involving electromagnetic or electrical stimulation should not automatically be interpreted as evidence for every EMS system or for every urinary condition.
Published by: Incontinence Direct Content Team
Last reviewed: September 2026